How David Curran’s frightening journey from feeling healthy to quadruple bypass surgery exposes a deeper healthcare contradiction: a system can deliver extraordinary treatment while making patients work too hard to be heard.
“Too often, PWLE are asked to share their stories but excluded from decisions. Meaningful engagement extends beyond simply being heard.” — World Health Organization, World Mental Health Day 2026: Lived experiences heard: real voices, real change.
David Curran’s coronary calcium score of 2,627 changed everything. His story raises a difficult question about healthcare’s design: why must patients sometimes fight to be heard while physicians and clinic staff spend hours navigating administrative complexity? From the ICU bedside to AI-powered medical billing, the opportunity is not simply to automate more work. It is to prevent avoidable friction before it begins.
The patient who had to prepare a legal argument to get his heart checked
David Curran was trying to live his life. He played tennis, hiked in Tilden Park, and believed he was reasonably healthy.
Then his breathing began to deteriorate.
He had a family history that should have made the issue especially concerning. Three grandparents had died of heart attacks. His mother had died of one. His father had undergone open-heart surgery. His sister had recently been hospitalized with an enlarged heart.
Yet getting a cardiology referral from his HMO primary-care physician had been an ongoing struggle.
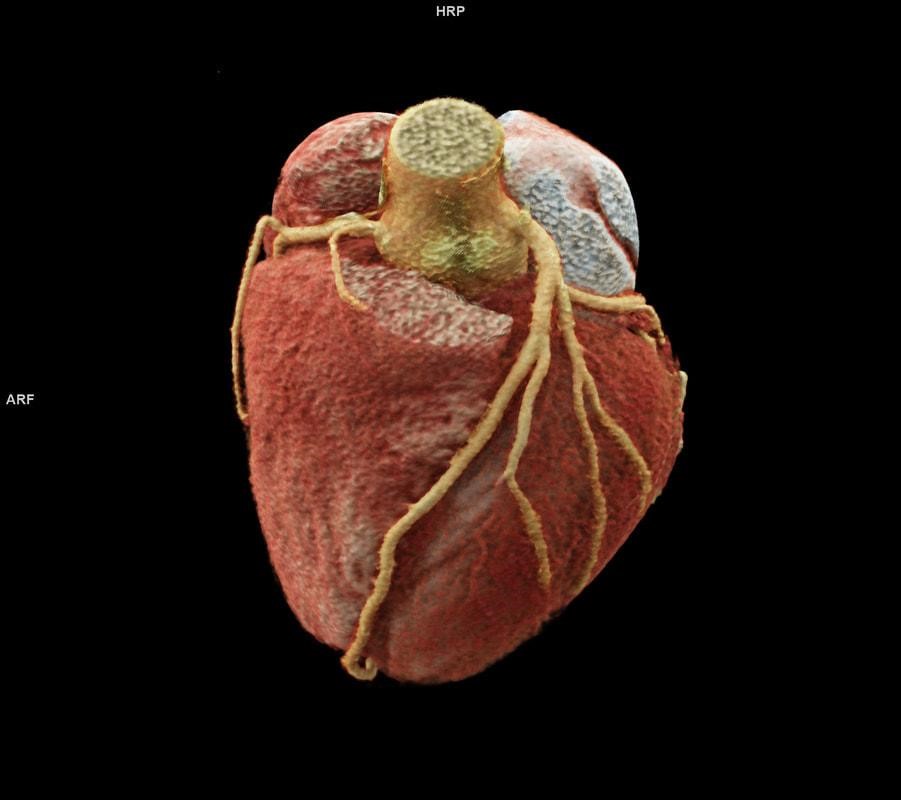
Curran eventually advocated for a coronary calcium scan. His score was 2,627, in the 98th percentile. Further testing revealed severe coronary artery disease, including a completely blocked artery. What initially seemed like a possible stent became a quadruple bypass operation.
In his October 11, 2026, first-person account for SFGATE, Curran describes the fear, frustration, dark humor, and human kindness that accompanied his journey.
One detail stands out. Before his appointment, he had prepared to argue for further evaluation, presenting his family history and worsening symptoms. He described the experience as having to prepare an argument almost as if he were going to court.
A medical appointment should not feel like a courtroom drama in which the patient must prove that a symptom deserves attention.
Of course, good medicine does not mean ordering every test a patient requests. Clinical judgment, evidence, risk assessment, and appropriate testing all matter. We also do not have the complete medical record or every consideration behind the decisions in Curran’s case.
But his account raises a question that deserves serious attention:
Why can a patient sometimes have to work so hard to get a concern investigated, only to have the system move at extraordinary speed once the danger becomes unmistakable?
Healthcare can be remarkably sophisticated at treating a crisis.
It should also be capable of making the path to appropriate evaluation less difficult to navigate.
Curran’s story is not proof that every doctor dismisses symptoms or that every healthcare organization operates this way. It is a human account of one patient’s experience—and an opportunity to examine the systems surrounding care.
The uncomfortable question is whether we have become better at responding to emergencies than at listening before they happen.
A score of 2,627—and absolutely no reason to celebrate
In school, a high score is good news.
Curran’s coronary calcium score was 2,627.
This was not the kind of achievement his mother had hoped he would earn.
His humor makes the number memorable, but the medical situation was serious. A coronary calcium score measures calcified plaque in the coronary arteries and helps clinicians assess coronary atherosclerotic burden in the appropriate clinical context. It is not, by itself, a complete diagnosis or a guarantee of what will happen next.
Curran’s subsequent evaluation revealed severe blockages requiring surgery.
The lesson is not that one particular test should be ordered for every person. Testing decisions depend on individual symptoms, risk factors, clinical guidance, and professional judgment.
The lesson is that symptoms, history, and changing circumstances deserve appropriate attention—and that patients need a clear path toward evaluation when concerns warrant it.
A test can produce a result in minutes. Understanding that result, communicating its implications, coordinating follow-up, and helping a frightened patient make decisions require something more than a number on a screen.
Healthcare is not merely the production of information.
It is the ability to move the right information to the right person, at the right time, with the right context and a meaningful next step.
A diagnostic system can be technically excellent while the surrounding process remains difficult to navigate.
The same distinction matters in medical practices. A billing system can process a claim correctly when all the necessary information is present. But if the information is incomplete, inconsistent, or delayed, the people downstream may have to spend time reconstructing what should have been clear from the beginning.
Different clinical and administrative problems require different solutions. Yet both remind us that the quality of a system depends on more than the capabilities of its individual tools.
Marcella: The human intelligence no dashboard can replace
After his operation, Curran woke in the intensive care unit facing a reality far removed from his former routine.
Breathing was difficult. Moving was uncomfortable. Eating required effort. Even small activities became accomplishments.
Then there was Marcella, the ICU nurse identified by first name in his article.
Curran describes her as experienced, engaged, practical, and kind. She helped him eat, showed him how maple syrup could make his oatmeal more tolerable, offered advice on taking his pills, and coached him through breathing exercises. She also helped him begin walking again.
These details are not incidental.
They show what care looks like when it reaches beyond a checklist and responds to the person experiencing the illness.
There was no grand technological breakthrough in the maple syrup. No sophisticated algorithm was needed to understand that a patient who had just undergone major surgery might need a little help making hospital food tolerable.
The intervention was small. The difference it made to Curran was not.
Technology can monitor oxygen saturation, display vital signs, record medication administration, and organize clinical information. These capabilities matter. But they do not make the patient’s experience interchangeable with the data describing it.
Marcella helped Curran through a frightening and physically vulnerable experience. Her attention mattered because she was present, understood what he was facing, and could respond.
The point of healthcare technology should not be to make human attention unnecessary. It should be to make human attention available where it matters most.
That is a useful test for every new healthcare tool.
Does it remove repetitive work and give people more time to care? Or does it add another screen, another alert, another reconciliation task, and another reason to look away from the person in front of them?
Automation is valuable when it improves the work. It is less impressive when it simply relocates the burden.
The objective should not be a hospital or medical practice in which nobody needs help.
It should be a system in which the people who provide that help have better information, fewer avoidable obstacles, and more time to do it well.
The other David: A reminder that we rarely see the whole system
Curran’s account includes another patient, also named David, who experienced postoperative confusion and delirium.
Separated by a curtain, Curran heard the other patient repeating that he was David and that he was very funny. Nurses, physicians, and family members came in and out of the neighboring space.
Curran, hungry, uncomfortable, and eager for assistance, initially wondered why the other patient was receiving so much attention while he waited for a blanket and something to eat.
Then he realized that the other David was confused and required close observation.
The moment is funny because Curran does not portray himself as a perfectly patient patient. He admits to the irritation and petty thoughts that can arise when someone is uncomfortable and feels overlooked.
But there is a deeper lesson.
From one side of a curtain, it can look as though someone is receiving unnecessary attention. From the other side, the situation may involve a patient who is disoriented and needs monitoring.
One person sees a delay. Another sees a clinical priority.
Neither person necessarily has the whole picture.
This happens outside hospitals, too.
A physician may believe a billing specialist has all the documentation needed to submit a claim. The billing specialist may be waiting for a missing detail. An administrator may believe an authorization has been completed, while a clinician is still waiting for confirmation.
Everyone may be working hard. Everyone may be frustrated. The system may still be failing to provide a shared understanding of what needs to happen next.
The answer is not to assume that one person is lazy, careless, or incompetent.
It is to design processes that make relevant information visible, clarify responsibility, and reduce unnecessary handoffs.
Sometimes, the problem is not that people are failing to do their jobs.
It is that the system makes doing the right job harder than it needs to be.
Healthcare has plenty of technology. Why is there still so much friction?
Healthcare has electronic health records, practice-management systems, scheduling software, patient portals, clearinghouses, payer portals, analytics platforms, and a rapidly expanding collection of AI tools.
And yet, clinicians and administrative staff still spend substantial time searching for information, entering data, correcting errors, reconciling discrepancies, and following up on unfinished tasks.
We have digitized a great deal of healthcare.
We have not necessarily simplified it.
A phone call becomes a portal message. A paper form becomes a digital field. A manual handoff becomes an automated notification. A missing piece of information becomes a work queue.
The process looks more modern. The burden may remain.
This is the difference between digitizing an activity and redesigning the system that produces it.
Consider a medical practice in which information is entered into one system, transferred to another, reviewed by a third party, and re-entered somewhere else. Each tool may function as intended. But every transition creates an opportunity for information to be lost, changed, duplicated, or misunderstood.
If something goes wrong, someone must investigate.
If it happens repeatedly, someone must investigate repeatedly.
Eventually, the practice may buy another tool to make those investigations faster.
That tool might be helpful. But a more fundamental question remains unanswered:
Why does the same problem keep occurring?
A faster mop is useful when the floor gets wet. It is not a complete solution when the pipe keeps leaking.
Healthcare sometimes invests heavily in the mop.
The administrative burden is measurable
This is not simply a complaint about inconvenient software or paperwork that nobody enjoys.
Administrative requirements consume real time.
The American Medical Association’s May 2026 report on prior authorization described findings from its survey of 1,000 physicians. Among the reported results:
- Physicians handled an average of 40 prior authorization requests per week.
- Physicians and staff spent approximately 13 hours each week on prior authorization.
- 94% of surveyed physicians said prior authorization contributes to burnout.
- 95% said prior authorization delays access to necessary care.
- 79% reported that patients abandon treatment because of prior authorization challenges.
These are survey findings, not universal measurements of every practice. Prior authorization is also not the same as medical billing, and the two should not be treated as interchangeable.
However, the results illustrate the wider issue: healthcare professionals spend substantial time navigating administrative processes that can interfere with access, efficiency, and attention.
The broader financial context is enormous. The Centers for Medicare & Medicaid Services reported that U.S. healthcare spending reached $5.3 trillion in 2024, equivalent to 18% of gross domestic product. That figure includes the full range of healthcare spending; it is not an estimate of administrative waste. CMS National Health Expenditure data.
The important question is not whether healthcare can eliminate all administrative work. It cannot, nor should it. Documentation, payment integrity, clinical review, privacy, and accountability are essential.
The question is how much repetitive work is necessary—and how much exists because the systems responsible for coordinating that work were not designed to function well together.
For smaller physician-owned practices, this distinction can be especially important. They may have fewer staff members to absorb exceptions, less capacity to build custom integrations, and limited time to evaluate competing software.
A recurring administrative problem does not disappear because the clinic is busy treating patients.
Someone still has to fix it.
And if the same problem returns next week, someone has to fix it again.
The contrarian argument: Stop measuring progress only by speed
Healthcare technology often promises faster work.
Faster documentation. Faster coding. Faster claims. Faster eligibility checks. Faster denial management.
Speed matters. But it is not the only measure of value.
If a task is necessary, making it faster can be useful.
If a task exists because information was captured incorrectly, making the correction faster may help—but it does not address the original cause.
If two systems disagree, moving the disagreement from one platform to another in milliseconds is not the same as resolving it.
If staff must repeatedly reconcile inconsistent information, a dashboard showing the work in real time may improve visibility without reducing the work itself.
We should not dismiss those improvements. Visibility, speed, and automation can make a meaningful difference. But we should ask whether they solve the underlying problem or merely make it easier to manage.
The next stage of healthcare automation should ask not only, “How do we do this faster?” but also, “Why do we keep having to do this?”
That question changes the starting point.
Instead of beginning with a task to automate, begin with the problem that generates the task.
Where does the information originate? What is required? What is missing? Where does context disappear? Why does someone need to intervene? Could the same issue have been prevented earlier?
This is harder than adding a new feature because it requires examining the entire process.
It also demands intellectual honesty. Some problems arise from legitimate clinical complexity, payer rules, coverage decisions, or regulatory requirements. Not every exception is preventable, and not every denial signals a system failure.
The objective is to distinguish necessary complexity from avoidable complexity.
That is where good process design and well-targeted AI can make a difference.
Medical billing: The problem may begin before the claim exists
Curran’s story concerns his health, diagnostic evaluation, surgery, and recovery. It does not establish that medical billing caused his delayed referral or his cardiac condition. It would be misleading to claim otherwise.
The connection is a broader one: healthcare depends on information moving through complex systems, and friction can consume the time and attention of the people who rely on those systems.
Medical billing is one place where this becomes visible.
A clinical encounter generates information. That information must be documented, translated into the appropriate codes and claim data, checked against applicable requirements, and submitted through the relevant processes. Depending on the practice and payer, the claim may pass through practice-management software, a clearinghouse, and payer systems.
When the information is incomplete or inconsistent, the process may require additional review, correction, resubmission, or follow-up.
Some of that work is unavoidable. Claims must accurately represent services provided and meet applicable requirements. Human review remains important where clinical interpretation, judgment, or accountability is needed.
But some rework can arise from preventable problems.
A required detail may not have been captured. Information may be inconsistent across systems. A handoff may not communicate what the next person needs. A recurring exception may be treated as an isolated incident rather than a pattern worth correcting.
The result is an administrative burden that extends beyond one claim.
For a small practice, every hour spent resolving avoidable exceptions is an hour that cannot be spent on another operational priority. Staff may still provide excellent service, but they are doing so while managing a process that repeatedly demands their attention.
The central question for medical billing technology is therefore bigger than processing speed.
Can the technology help practices identify and prevent recurring information problems earlier in the revenue cycle?
That is a more demanding goal than automating the last step.
It requires understanding how information is created, how it moves, what the downstream process requires, and where avoidable inconsistencies originate.
OnnX: Don’t just automate the mess. Prevent the mess.
This is the problem OnnX is designed to address.
OnnX is an AI-powered healthcare revenue-cycle intelligence platform focused on improving the upstream structure and quality of clinical and operational information that supports medical billing.
Its central premise is that some downstream billing problems begin upstream—before a claim is submitted.
When information is incomplete, inconsistent, or poorly structured, downstream teams may have to repair problems they did not create. Automation can help them work faster, but a stronger approach is to identify recurring problems earlier and reduce the conditions that cause avoidable rework.
This is not a promise that every denial can be prevented or every claim will be paid. Payer policies, coverage decisions, clinical complexity, and legitimate documentation requirements will continue to matter.
It is a different way to frame the problem.
Instead of looking only at the rejected claim, ask what made the rejection possible.
Instead of treating every correction as an isolated task, look for patterns.
Instead of adding another tool to the end of a fragmented process, examine whether the information entering that process can be made more reliable.
For a small medical practice, that could mean asking:
- Which recurring billing problems consume the most staff time?
- Which problems originate in missing or inconsistent information?
- Which corrections are repeated because the same issue keeps returning?
- Which handoffs create delays or confusion?
- What can be validated earlier without adding unnecessary burden to clinicians?
- Where should AI assist, and where should a qualified human remain responsible?
These questions move the discussion from simply processing work to understanding why the work exists.
The goal is not to replace every person involved in billing. It is to reduce avoidable administrative effort so that the people who manage the revenue cycle can focus on work that genuinely requires their expertise.
The most useful AI may not be the AI that completes the most tasks. It may be the AI that helps a practice stop needing so many corrective tasks in the first place.
That is the difference between automating a mess and designing a better system.
Three questions every healthcare leader should ask before buying more AI
1. Are we eliminating work—or simply making it faster?
Before automating a task, establish why it exists.
Is it necessary for safety, compliance, clinical judgment, or payment integrity? Or does it repeatedly occur because information is missing, duplicated, inconsistent, or difficult to locate?
Necessary work deserves better tools.
Unnecessary work deserves investigation before it receives a larger technology budget.
2. Can we identify the source of recurring errors?
A denial report can reveal what happened to a claim. It may not explain the full chain of events that led to the problem.
Track recurring exception categories and distinguish payer-driven issues from documentation gaps, data-quality problems, workflow failures, and other causes.
The goal is not to assign blame to an individual. It is to discover which conditions keep generating the same work.
3. Does the technology return attention to people?
Measure more than processing speed.
Does the system reduce duplicate entry? Make missing information visible earlier? Improve handoffs? Reduce repeated corrections? Help staff find relevant context more quickly?
Does it preserve appropriate human review and make errors easier to identify and correct?
If a new tool reduces one task but creates three others, its actual value may be considerably smaller than the product demonstration suggested.
The right measure of progress is not how much technology a practice uses. It is how much meaningful improvement the technology delivers.
Four myths keeping healthcare stuck
Myth 1: More automation automatically means less work.
Not necessarily. Automation can accelerate a poorly designed process or reproduce errors at scale. The quality of the inputs and the design of the process still matter.
Myth 2: Every billing problem is a denial-management problem.
A denial is an outcome, not a complete explanation. Its cause may involve documentation, eligibility, coding, coverage rules, claim construction, timing, or other factors. Effective improvement requires identifying the cause rather than treating every denial as identical.
Myth 3: Human attention is the part of healthcare technology should eliminate.
Human attention is often the resource healthcare most needs to preserve. Technology should reduce repetitive administrative work while supporting the judgment, empathy, and problem-solving that patients and clinicians depend on.
Myth 4: Patients can solve system problems by advocating more forcefully.
Self-advocacy can be valuable. But it should not be the only mechanism through which concerns receive attention.
Patients differ in their time, confidence, health literacy, language access, resources, and ability to navigate complex organizations. A process that works only when someone knows how to push repeatedly is not equally accessible to everyone.
What practices can do now—without buying another platform
Healthcare organizations can begin reducing avoidable friction before making a major technology investment.
Map one recurring problem. Choose a common billing exception or repeated handoff. Trace the process from the original information to the final outcome. Identify every point where the information changes, gets checked, or requires intervention.
Separate the symptom from the cause. A delayed claim is a symptom. The cause might be missing information, a payer requirement, a system-interface problem, or a process that depends on manual follow-up. Investigate before prescribing a solution.
Measure repeat work. Track the most common correction categories, the time required to resolve them, the number of repeated handoffs, and how often the same issue returns. Establish a baseline before changing the process.
Improve information quality at the point of capture. Where practical, make necessary information easier to record correctly and validate early. Avoid adding fields or steps that create unnecessary work for clinicians.
Listen to the people doing the work. Billing staff, clinical teams, and administrators often see recurring failures long before those failures appear in a leadership dashboard. Give them a practical way to identify patterns without turning every discussion into a blame exercise.
Preserve appropriate human oversight. Automation should support professional judgment and accountability, not obscure how a decision was reached or make it harder to correct an error.
Reassess after implementation. A tool should be evaluated in the real environment where it is used. If it reduces one category of work but creates another, measure the net effect rather than counting only the tasks it automates.
The goal is not to eliminate every administrative process. It is to make necessary work more reliable and proportionate while identifying work that should not have to recur.
The future of healthcare depends on more than smarter software
Curran’s account is memorable because it is not a technology success story.
It is a story about a person confronting a frightening diagnosis, the uncertainty of surgery, the vulnerability of intensive care, and the people who helped him recover.
Marcella mattered because she paid attention. The other patients mattered because their experiences revealed how much of healthcare happens beyond a chart or monitor. Curran’s own reflections mattered because he described both the failures and the moments of kindness without pretending the experience was simple.
Technology can help organize healthcare. It can improve access to information, identify patterns, support workflows, and reduce repetitive administrative tasks.
But technology is not the mission.
A hospital is not successful because it has more software. A medical practice is not successful because its staff can process more administrative work. A revenue cycle is not necessarily healthy because it has a dashboard for every exception.
The point is to support good care, reliable operations, and appropriate payment while reducing avoidable burdens on the people involved.
For AI companies, this requires resisting the temptation to treat every problem as an invitation to automate another task.
Sometimes the right answer is better information. Sometimes it is a clearer process. Sometimes it is improved coordination. Sometimes the work is necessary and should simply be made easier to complete.
The important thing is to know the difference.
For OnnX, that means approaching revenue-cycle intelligence from upstream: improving the information and processes that shape billing outcomes, rather than focusing only on the corrections required after a problem appears.
The opportunity is not to promise a frictionless healthcare system. Healthcare is too complex for that.
It is to make preventable friction less common—and to give people more time for the work that cannot be reduced to a transaction.
The final contradiction
David Curran’s journey from feeling healthy to quadruple bypass surgery is a powerful reminder of the importance of listening, clinical judgment, patient advocacy, and human care.
It does not prove that billing technology could have prevented his cardiac crisis. His account does not establish that connection, and it should not be used to make one.
But it does invite a broader question about how healthcare is designed.
Why do we celebrate systems that can respond to a crisis while tolerating processes that make people work unnecessarily hard to navigate the system before, during, and after that crisis?
Why do we invest in making work faster without always asking whether the work needs to exist?
And why do we sometimes treat administrative complexity as inevitable when some of it may be the result of preventable design choices?
The answers will vary across clinical care, hospital operations, and medical billing. Not all complexity is waste. Safety, accuracy, privacy, and accountability require real work.
But healthcare should be willing to examine its own processes with the same rigor it applies to clinical problems.
The patient is not the workflow.
The claim is not the purpose.
And administrative activity is not the same as value.
The next breakthrough may not be another system that automates the work we have accumulated. It may be a system that helps us understand which work is necessary, which work can be simplified, and which work should never have been created in the first place.
What if the most meaningful use of AI in healthcare is not teaching machines to do more work—but helping healthcare stop creating unnecessary work for people?
I would welcome perspectives from physicians, clinic owners, nurses, billing professionals, and healthcare technology leaders: Which recurring administrative task in healthcare do you believe should not exist in its current form?
Share your experience in the comments, and repost this article if you believe healthcare technology should create more room for care—not simply more efficient bureaucracy.
Explore the free resource in the Featured section of my LinkedIn profile. No signup required.
About the author
Dr. Daniel Cham, MD, is a physician, healthcare consultant, and entrepreneur focused on the intersection of medical practice, healthcare technology, and medical billing. Through his work on OnnX, an AI-powered medical billing and revenue-cycle intelligence platform for small and medium-sized clinics, he explores how better-structured information and better-designed processes can reduce avoidable administrative friction.
Follow the conversation:
References and further reading
- David Curran, SFGATE, “How I went from ‘healthy’ to a quadruple bypass in weeks”, October 11, 2026.
- World Health Organization, “World Mental Health Day 2026: Lived experiences heard: real voices, real change”, October 10, 2026.
- American Medical Association, “AMA survey: Prior authorization reform pledge falls short with physicians”, May 13, 2026.
- Centers for Medicare & Medicaid Services, National Health Expenditure data fact sheet.
Disclaimer
This article provides general educational commentary on healthcare operations, technology, and administrative design. It is not medical, legal, coding, billing, financial, or compliance advice. The discussion of David Curran’s experience is based on his published personal account and should not be interpreted as an independent clinical assessment of his care. Individual medical decisions depend on the patient’s circumstances and the judgment of qualified healthcare professionals.
#Healthcare #HealthTech #AIinHealthcare #MedicalBilling #HealthcareAI #RevenueCycleManagement #RCM #PhysicianEntrepreneur #DigitalHealth #HealthcareInnovation #PatientAdvocacy #ClinicalWorkflow #DataQuality #OnnX
Leave a Reply