One family’s extraordinary journey raises an uncomfortable question: If healthcare exists to help people reclaim their lives, why do we tolerate systems that repeatedly take physicians away from the people they are trying to help?
“They all go back to the importance of the patient-physician interaction, which is really just a human connection that’s part of delivering good-quality care and getting good outcomes.” — Dr. Gary Price, President of The Physicians Foundation, speaking to Medical Economics
A brother stepped forward before his sister asked
Stephanie Johnson lived with polycystic liver disease. Her liver had enlarged so dramatically that everyday activities became difficult. Eating was uncomfortable. Climbing stairs left her breathless. Strangers sometimes mistook her enlarged abdomen for pregnancy.
Her younger brother, Marcus Brown, wanted to help.
Stephanie was reluctant to ask family members to donate an organ. She believed other people on the transplant waiting list might need a liver more urgently.
Marcus saw it differently.
He raised the possibility of donating part of his liver with their mother before Stephanie knew what he was considering.
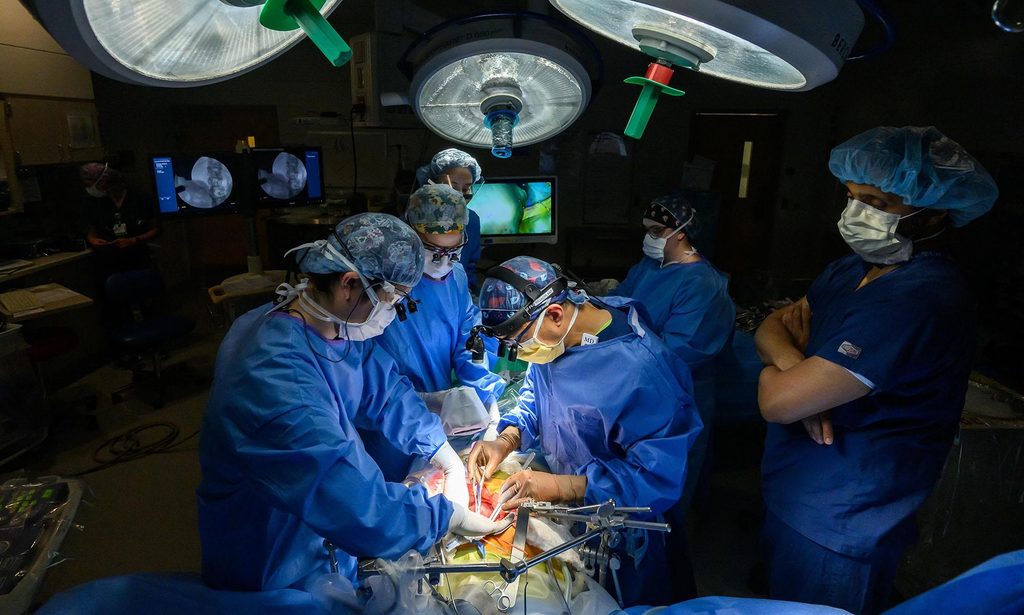
In February 2026, Marcus donated part of his liver to his sister at VCU Health’s Hume-Lee Transplant Center in Richmond, Virginia.
The operation involved a multidisciplinary medical team, including transplant surgeon Dr. Seung Duk Lee, M.D., Ph.D., and Dr. David Bruno, M.D., FACS. During Stephanie’s recovery, doctors also discovered a cancerous growth in her colon. Surgical oncologist Dr. Leopoldo Fernandez subsequently removed it.
Stephanie endured a prolonged hospitalization before finally returning home.
Then came a small moment with enormous meaning.
She found herself running up the stairs.
Previously, climbing them had left her struggling for breath. Now, she could move more freely, eat more comfortably, and begin reclaiming ordinary parts of life.
She could buy clothes in her own size. She could focus more of her energy on her two sons.
The medical procedures were extraordinary. The victories that mattered to Stephanie were wonderfully ordinary.
Eating a meal. Climbing stairs. Wearing a shirt without trying to hide. Getting more of your life back.
Her story is about family, medical expertise, difficult decisions, and the possibility of recovery.
It is not a story about medical billing, and there is no evidence that billing problems caused or affected her outcome.
But it reminds us of a principle that should guide every part of healthcare:
The system exists to serve the patient. The patient does not exist to serve the system.
That sounds obvious.
So why is it so easy to lose sight of it?
The uncomfortable question: What is healthcare optimizing for?
Healthcare can perform extraordinarily complex operations. Surgeons can remove diseased organs and transplant donated tissue. Clinical teams coordinate medications, imaging, laboratory results, intensive monitoring, and recovery.
Yet many physicians and their staff still spend hours tracking down missing information, correcting preventable errors, checking authorization requirements, and trying to understand why a claim has become another administrative project.
We can perform miracles in the operating room and still struggle to get the right information to the right person at the right time.
That is not an argument against technology, administration, or necessary safeguards.
It is a question about priorities.
Are we optimizing healthcare for the delivery of care—or for the processing of everything that surrounds it?
There is a difference.
A system can become extremely efficient at processing paperwork while leaving the underlying reasons for that paperwork untouched.
It can generate a dashboard showing yesterday’s failures without preventing tomorrow’s.
It can automate a process that should have been simplified.
It can even use artificial intelligence to make a bad workflow faster.
Congratulations. We have successfully taught the machine to run in circles.
The harder question is whether the circle needed to exist.
The contrarian thesis: Some billing problems begin before billing
As a physician and founder of OnnX, I have become increasingly interested in a question that sits upstream of traditional revenue-cycle management.
What if some of the work we call billing is actually the work of reconstructing information that should have been complete, connected, and usable much earlier?
Consider a typical patient encounter.
A patient schedules an appointment. The practice collects demographic and insurance information. Staff check eligibility and determine whether a referral or authorization is required. The physician evaluates the patient and documents the encounter. Coding and charge capture follow, and a claim is submitted.
Each stage depends on information from earlier stages.
A missing detail may not be obvious when it first appears. The workflow continues. Someone else assumes the information is complete. The problem becomes visible only when the next step fails.
Now someone must investigate.
Was the insurance information correct? Was authorization required? Did the referral arrive? Does the documentation support the intended service? Was a payer-specific requirement overlooked? Did the information exist in another system but fail to reach the person who needed it?
The claim becomes the crime scene.
The actual cause may be several steps away.
This is why I believe healthcare should investigate the origin of recurring errors, not simply optimize the department that discovers them.
A denial is an event. It is not always an explanation.
A coding query is a task. It does not automatically reveal why the documentation was unclear.
A delayed payment is an outcome. It does not tell us whether the original problem began with registration, coverage, authorization, documentation, coding, or payer processing.
The location where a problem appears is not necessarily where it began.
That distinction can change how a practice measures performance, allocates staff, selects technology, and decides which problems deserve attention first.
The hidden tax of administrative rework
Imagine a hypothetical physician-owned practice.
A physician sees a patient, makes a clinical decision, and documents the encounter. The practice expects to submit an appropriate claim.
But the insurance information is incomplete. A referral requirement was overlooked. The documentation needs clarification.
Each issue appears manageable.
Together, they create a chain of additional work.
A staff member must identify the problem, determine what is missing, contact someone, retrieve information, and correct the record. The physician may need to clarify documentation. The claim may be delayed, corrected, or denied.
The practice has now paid for the encounter in operational terms twice: once to deliver care and again to repair the process around it.
Sometimes more than twice.
There may be staff time, physician interruptions, additional communication, delayed cash flow, and patient frustration.
These costs are scattered across departments. Because no single line item captures the entire burden, the practice may underestimate what recurring information failures actually cost.
The hidden tax is the labor required to reconstruct information that was missing, disconnected, misunderstood, or not preserved in context.
Not every billing problem originates upstream. Some result from payer decisions, contractual disputes, changing rules, genuine coding disagreements, or other causes outside a practice’s direct control.
But that makes root-cause analysis more important, not less.
If the practice does not distinguish between problems it can prevent and problems it must resolve, it may spend money trying to fix the wrong thing.
The numbers: Administrative burden is not imaginary
The American Medical Association’s 2024 prior authorization survey reported that physicians and their staff spent an average of approximately 13 hours per week completing prior authorization work, with physicians completing an average of 43 prior authorizations weekly.
The survey also found that physicians overwhelmingly viewed prior authorization as contributing to burnout and delaying necessary care.
These figures describe a specific survey and should not be treated as universal measurements for every practice. But they illustrate the scale of the challenge.
Thirteen hours is not a rounding error.
It is more than a working day every week.
And the cost is not simply the salary of the person completing the authorization. It includes the opportunity cost of what that person could have done instead.
Could a coordinator have helped a patient understand the next step in treatment? Could a medical assistant have supported follow-up? Could a physician have reviewed a complex case without another interruption?
We should not assume that every saved administrative hour automatically becomes a clinical hour. Staffing, scheduling, and practice economics are complicated.
But we should ask a straightforward question:
If a process consumes hours every week, what evidence tells us that those hours are being spent in the best possible way?
A timely warning from Dr. Gary Price
In an interview published October 20, 2026, Medical Economics spoke with Dr. Gary Price, president of The Physicians Foundation, about misinformation, burnout, and declining trust between patients and physicians.
Price emphasized the importance of preserving time for the patient-physician relationship. He also discussed how fragmentation, insurance barriers, prior authorizations, and denials can interfere with that relationship.
His argument is important because it moves the conversation beyond physician dissatisfaction.
Time with patients is not a luxury feature of healthcare. It is part of how healthcare works.
A physician who has enough time to listen may discover something that changes a diagnosis or treatment plan. A physician who can explain uncertainty may help a patient make a better-informed decision. A physician who knows the patient’s history may recognize a change that a fragmented encounter obscures.
The human connection is not separate from clinical quality.
Yet administrative systems can consume the very time that helps make clinical care effective.
This is not a call to eliminate every administrative requirement. Some protect patients, support appropriate utilization, and establish accountability.
The challenge is to distinguish necessary controls from avoidable friction—and then design the necessary controls as well as possible.
The objective should not be to eliminate administration at any cost. It should be to eliminate the administration that exists because the system repeatedly fails to work as intended.
Three perspectives that belong in the same conversation
1. Dr. Gary Price: Protect the human connection
Price’s recent comments emphasize that physician-patient interaction and trust are fundamental to good care.
The operational implication is clear: administrative processes should support the clinical relationship, not compete with it unnecessarily.
A technology that saves time is valuable only if it produces a meaningful improvement in the work or experience that matters.
2. The American Medical Association: Measure the administrative burden
The AMA’s prior authorization research gives physicians a way to discuss the burden using more than anecdotes.
The implication is that practices should measure the time spent on repetitive administrative tasks, identify where delays originate, and evaluate whether interventions actually reduce the burden.
“Everyone feels overwhelmed” is a reason to investigate.
It is not yet a diagnosis of the operational problem.
3. CMS: Improve information exchange and standardization
The Centers for Medicare & Medicaid Services has established interoperability and electronic prior authorization requirements for certain impacted payers through its CMS Interoperability and Prior Authorization Final Rule.
These changes aim to improve information exchange and make prior authorization processes more transparent and efficient. Requirements and implementation timelines vary by provision and organization.
The implication is that electronic exchange matters—but digitization alone is not the finish line.
An electronic form can still request redundant information. An automated process can still depend on incomplete data. A faster transaction can still fail if the underlying requirement is misunderstood.
Digitization changes the channel. Better information structure can change the quality of the exchange.
These perspectives are not endorsements of OnnX. They represent different parts of the healthcare landscape that converge on a common question: how do we make the system support care more effectively?
The OnnX thesis: Fix the signal before repairing the noise
OnnX is an upstream intelligence platform for healthcare, built by physicians and medical billers to reduce downstream administrative and billing noise so physicians can focus on clinical care.
Our premise is that some recurring billing problems begin with fragmented information, unclear requirements, or disconnected decisions before a claim is submitted.
The working process is:
Capture → Structure → Preserve → Propagate → Act → Learn
- Capture: Collect relevant information where it first becomes available.
- Structure: Organize the information so its meaning and relationships are clear.
- Preserve: Retain the context needed to interpret it correctly.
- Propagate: Make the relevant information available to the next appropriate step.
- Act: Identify gaps, inconsistencies, or requirements that need attention.
- Learn: Review outcomes and use verified patterns to improve future decisions.
The objective is not to replace medical billers or promise that every denial will disappear.
It is to test whether better information continuity and earlier decision support can prevent some of the rework that practices currently resolve downstream.
Think of a recurring billing error as a smoke alarm.
One option is to hire someone to reset it every time it sounds.
Another is to investigate whether something is repeatedly causing the alarm to activate.
The first task may still be necessary. But if nobody investigates the cause, the practice has created a very efficient alarm-resetting department.
That is not the same as solving the problem.
Seven practical steps for physician-owned practices
A practice does not need to purchase another platform tomorrow to start improving its information quality.
Begin with one recurring problem.
1. Pick a specific failure.
Choose something measurable, such as recurring eligibility errors, missing authorization information, documentation clarification requests, or claims returned for incomplete data. “Fix billing” is not a useful project definition.
2. Map the information journey.
Document where the information originates, who handles it, where it is stored, and when it is needed. Ask frontline staff where the process repeatedly breaks down.
3. Identify the earliest controllable cause.
Separate missing information from misunderstood requirements, unclear responsibilities, software limitations, and payer-side constraints. These problems require different interventions.
4. Establish a baseline.
Measure frequency, staff time, recurrence, and impact on claims or patient services. Without a baseline, a team can mistake a busy month for an improvement.
5. Fix the source where possible.
Improve the relevant registration field, documentation prompt, authorization process, responsibility assignment, or information exchange. Do not automatically send every problem to billing for repair.
6. Use technology for a defined purpose.
Automation may help flag missing fields, compare information, route exceptions, or surface relevant requirements. It should not invent clinical facts or silently make consequential decisions without appropriate oversight.
7. Evaluate honestly.
Check whether the intervention reduced the original problem, created new work, increased false alerts, or shifted the burden to another department. Expand only when the evidence supports it.
This approach is less glamorous than buying a platform with a futuristic name.
It is also more likely to reveal what the practice actually needs.
Metrics that matter more than a shiny dashboard
A useful operational improvement should be measurable.
Depending on the problem, consider tracking:
- First-pass claim acceptance: The proportion of claims accepted without correction, using a clearly defined measure.
- Preventable denial rate: The share of denials linked to causes the practice can reasonably address.
- Rework time: Staff time spent investigating, correcting, resubmitting, or escalating recurring issues.
- Missing-information rate: How often a workflow reaches a point where required information is absent or inaccessible.
- Authorization turnaround: The time required for practice-side processing, distinguished from payer processing time.
- Repeat-error rate: How frequently the same underlying issue returns after it has been corrected.
- Exception rate: How often an automated process needs human intervention.
- Patient communication burden: How often patients must contact the practice to clarify an administrative delay.
No single metric tells the whole story.
A lower denial rate might coincide with slower claim submission. An automated system might appear efficient because it fails to identify difficult cases. A new checking process might improve accuracy while increasing staff workload.
Pair efficiency measures with quality, safety, and workload measures.
The goal is not to make the dashboard green.
The goal is to make the underlying work better.
Five myths worth challenging
Myth 1: We just need better billers.
Good medical billers are essential. But even excellent staff cannot reliably compensate for every upstream information gap. When the same error recurs, investigate the process as well as the performance of the people working within it.
Myth 2: More automation means less work.
Automation can move work from one department to another, generate false alerts, or create new exception queues. Measure the entire workflow before and after implementation.
Myth 3: AI can solve documentation problems by generating more text.
More text does not necessarily mean better documentation. Accurate, relevant, clinically appropriate information matters more than note length. Clinicians remain responsible for ensuring that the record reflects the encounter truthfully.
Myth 4: Denials are simply part of doing business.
Some disputes and denials are unavoidable. That does not make every recurring denial inevitable. Classify the reasons, investigate the preventable portion, and track whether interventions reduce recurrence.
Myth 5: The newest platform must be the best solution.
Sometimes the right answer is software. Sometimes it is clearer training, a better template, a defined responsibility, or a simpler process. Buy technology to address a demonstrated problem—not to avoid diagnosing it.
The risks of getting it wrong
An upstream intelligence platform can create value, but it can also introduce new risks.
Clinical integrity: Never fabricate symptoms, findings, medical necessity, or other clinical information to satisfy a billing requirement.
Human oversight: Make recommendations understandable and provide a clear process for review, correction, and escalation.
Privacy and security: Apply appropriate safeguards, access controls, auditability, and agreements governing the use of patient information.
Bias and reliability: Test performance across specialties, payer arrangements, practice sizes, and patient populations. A system that works in one setting may fail in another.
Transparency: Users should understand why a system raised an alert and what evidence supports its recommendation.
Compliance: Practices should assess applicable HIPAA obligations, business associate arrangements, coding standards, payer contracts, and other requirements with qualified advisers.
Appropriate incentives: Do not encourage unnecessary services, unsupported diagnoses, or inflated coding in pursuit of better reimbursement.
There is a subtler risk: a system can make a bad process harder to question because it now has an algorithm.
An automated recommendation is not automatically correct. A workflow is not automatically appropriate because it is digital.
Technology should help people make better decisions—not obscure responsibility for those decisions.
A 30-day experiment
For a physician-owned practice, meaningful improvement can begin with a small, disciplined test.
Week 1 — Find the recurring problem. Choose one issue, gather examples, interview the staff handling it, and measure the baseline.
Week 2 — Trace it upstream. Identify where the information first becomes incomplete, inconsistent, inaccessible, or misunderstood. Separate internal causes from external constraints.
Week 3 — Test one intervention. Change a specific step, train the affected team, and define who handles exceptions. Keep the experiment limited enough to monitor safely.
Week 4 — Evaluate the evidence. Compare results with the baseline. Did the problem decline? Did workload actually fall? Did another error increase? Should the practice expand, modify, or abandon the intervention?
No giant transformation budget is required.
No presentation needs the phrase “paradigm shift.”
Just a real problem, a measurable test, and the willingness to discover that the original assumption may have been wrong.
What the future should look like
The future should not be a clinic where every employee spends the day supervising an endless parade of alerts.
Nor should it be a clinic where AI makes consequential decisions that nobody understands or checks.
A better future would allow relevant information to be captured appropriately, structured consistently, preserved with context, and made available to the people who need it.
Missing information would be identified earlier. Exceptions would reach the right person. Physicians would not repeatedly reconstruct details that already existed elsewhere. Medical billers could spend more time applying their expertise and less time chasing basic information.
Automation would handle appropriate routine tasks while people retained responsibility for decisions requiring judgment.
Success would be measured not by how many tasks software completed, but by whether accuracy improved, rework declined, operations became more predictable, and patients and staff had a better experience.
That is the direction behind OnnX: upstream billing intelligence.
The ambition is to investigate whether better information continuity and earlier decision support can reduce preventable downstream problems for physician-owned practices.
That is a hypothesis to validate through real workflows, measurable outcomes, and honest testing—not a promise that one platform can eliminate every problem.
Healthcare needs fewer confident promises and more disciplined investigations into where its problems begin.
The lesson Stephanie and Marcus leave us
Stephanie Johnson’s recovery is measured in things many healthy people rarely think about: eating a full meal, climbing stairs, buying clothes in her own size, and having more energy for her children.
Marcus Brown made an extraordinary personal decision to help his sister regain those ordinary freedoms.
Their family relied on a specialized medical team whose work demanded precision, coordination, and careful attention to both donor and recipient.
Their story reminds us that the purpose of healthcare is not merely to complete procedures, submit claims, or close tasks.
It is to help people live healthier lives.
Complex medicine will always require expertise, safeguards, and coordination. Not every administrative requirement can or should disappear.
But we should question avoidable friction wherever it repeatedly consumes the time, attention, and resources that patient care requires.
If a process is necessary, make it reliable.
If information is needed, make it available.
If an error keeps recurring, investigate its origin.
If technology is introduced, measure whether it improves the outcome.
And if physicians and staff are repeatedly asked to reconstruct information that was lost, duplicated, or poorly structured, ask whether the process needs to work that way at all.
The future of healthcare may depend not only on what we teach machines to do, but also on what we finally stop asking people to do over and over again.
A question for physicians, practice owners, and healthcare operators
If you could eliminate one recurring administrative problem from your practice tomorrow, which would give your team the most time back for patient care?
Prior authorization? Missing information? Documentation rework? Eligibility errors? Preventable denials?
Tell me in the comments. The most useful answers may come from the people who encounter these problems every day.
If this perspective resonates with you, share or repost it so more physicians and practice teams can join the conversation.
The goal is not to make administration disappear. It is to make unnecessary administration harder to justify.
Frequently asked questions
1. What is upstream billing intelligence?
It focuses on information quality, context, and decisions before a claim is submitted, with the aim of identifying gaps early enough to reduce avoidable downstream rework.
2. Is every medical billing denial preventable?
No. Denials can result from coverage limitations, payer decisions, contractual disputes, coding issues, incomplete information, and other causes. Practices should distinguish preventable problems from those requiring appeal or external resolution.
3. Does better documentation guarantee reimbursement?
No. Reimbursement also depends on coverage, applicable rules, authorization requirements, coding, contracts, and payer adjudication. Documentation must remain accurate and clinically appropriate.
4. Can AI eliminate prior authorization?
AI may help organize information, identify requirements, prepare submissions, and support status monitoring. It cannot eliminate payer requirements or guarantee approval.
5. How can a small practice begin reducing administrative burden?
Choose one recurring problem, measure its frequency and impact, trace it to its earliest controllable cause, and test a targeted improvement before expanding.
6. What should a practice measure?
Depending on the problem, measures may include first-pass claim acceptance, preventable denial rate, rework time, missing-information rate, authorization turnaround, repeat-error rate, and staff workload.
7. Does upstream intelligence replace medical billers?
It should not be framed as a replacement for billing expertise. Better information systems can help billers spend less time repairing avoidable gaps and more time applying their knowledge.
8. How is OnnX different from a traditional revenue-cycle management service?
OnnX is being developed around an upstream intelligence thesis: improve how information is captured, structured, preserved, and acted upon before it creates downstream billing problems.
9. Should every administrative process be automated?
No. Some processes protect safety, accountability, and compliance. The goal is to reduce unnecessary friction while preserving accuracy, privacy, appropriate review, and patient protections.
10. What is the first question to ask about recurring errors?
Where did this problem first become possible, and what information or decision would have prevented it?
About the author
Dr. Daniel Cham, MD, is a physician, entrepreneur, and founder working at the intersection of clinical care, healthcare operations, and technology. Through OnnX, he is exploring how upstream information quality and decision support can reduce administrative and billing friction for physician-owned practices.
Connect with Dr. Cham on LinkedIn.
Continue the conversation
Knowledge creates possibilities. Start by questioning one process, measuring one problem, and learning what could work better.
For a free resource, visit the Featured section of my LinkedIn profile. It is available without a signup.
Disclaimer
This article is for general educational and informational purposes. It is not medical, legal, coding, reimbursement, compliance, or financial advice. Requirements vary by payer, jurisdiction, specialty, and practice. Consult qualified professionals for guidance on specific circumstances.
References and further reading
- VCU Health: A brother’s liver donation gives his sister a new lease on life — the original account of Stephanie Johnson and Marcus Brown.
- Medical Economics: Misinformation, burnout and lost trust are “incredibly interrelated” — October 20, 2026, interview with Dr. Gary Price.
- American Medical Association: Prior Authorization — research and resources on prior authorization and physician burden.
- Centers for Medicare & Medicaid Services: CMS Interoperability and Prior Authorization Final Rule — federal requirements and implementation information.
#Healthcare #MedicalBilling #PhysicianEntrepreneur #HealthcareInnovation #PracticeManagement #HealthTech #PriorAuthorization #RevenueCycle #PhysicianOwnedPractices #PatientCenteredCare #OnnX
Leave a Reply